
What is the difference between 660 nm and 850 nm red light
· Published by Lumetive · 25 min read
Core Summary: The main difference between 660nm and 850nm red light is how deep the light travels and which tissues it reaches. 660nm is visible red light that is mostly absorbed within the outer layers of the skin, which is why it is used in face masks and other skin-focused devices and is widely studied for skin appearance. 850nm is invisible near-infrared (NIR) light that travels further into tissue, which is why it is common in body wraps and recovery-oriented devices and appears in musculoskeletal research. Both wavelengths are thought to act on the same cellular photoacceptor, cytochrome c oxidase in the mitochondria, and many devices combine the two. How much light actually reaches a given depth always depends on the device’s output, distance and exposure time.
How Two Wavelengths Target Different Tissue Depths
The fundamental difference between 660nm and 850nm red light lies in where each wavelength is absorbed. 660nm is a visible red wavelength that is largely absorbed in the skin and the tissue just beneath it. 850nm is an invisible near-infrared (NIR) wavelength that is absorbed less by skin pigments and blood, so a larger share of it passes through the surface to deeper layers such as fat and muscle.
Both fall within the “optical window” of biological tissue (roughly 600–1000nm), where light is not fully absorbed by water or hemoglobin. Photobiomodulation research proposes a shared mechanism for both — absorption by cytochrome c oxidase in mitochondria, linked to changes in cellular energy (ATP) production — but the two wavelengths deliver that light to different tissue depths.

Learn more: Cleveland Clinic — Red Light Therapy Overview · Hamblin MR (2016) — Photobiomodulation Mechanisms
How 660nm and 850nm Red Light Penetrate Tissue Differently
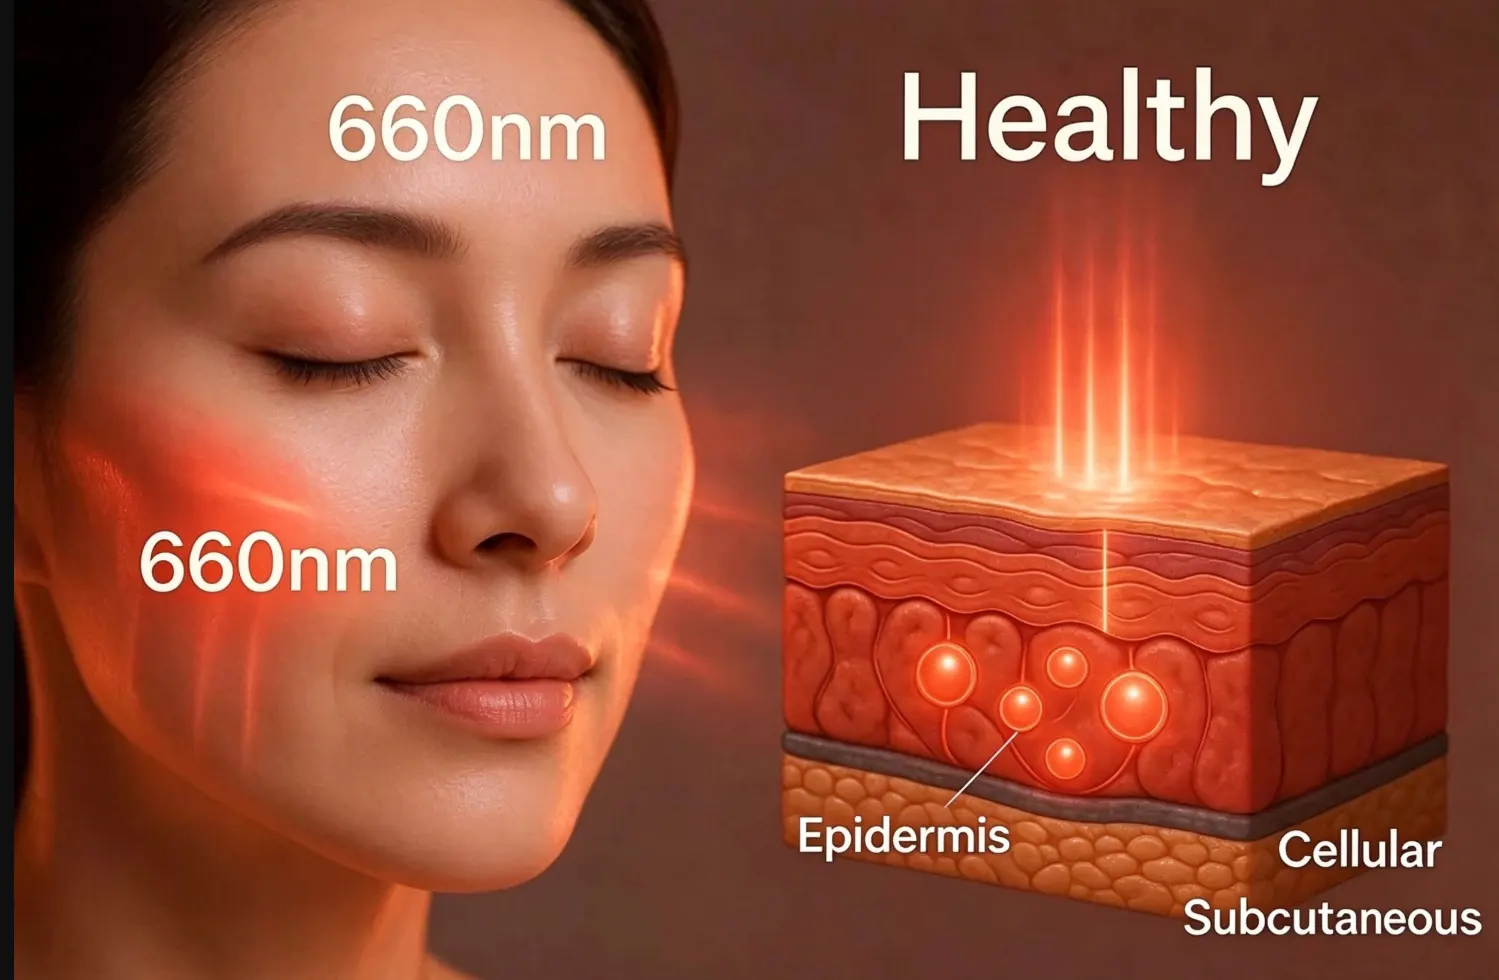
The difference in penetration is driven by how biological tissue absorbs and scatters light at different wavelengths. At 660nm, melanin and hemoglobin absorb a significant share of the light, so most of it is deposited in the epidermis and dermis. That is why 660nm is used for skin-focused applications, where target cells such as the collagen-producing fibroblasts of the dermis lie close to the surface.
At 850nm, absorption by melanin and hemoglobin drops sharply while water absorption stays low, so more of the light can pass through skin and fat into muscle. Optical models generally show near-infrared reaching several times deeper than visible red, although only a small fraction of the light arrives at the deepest layers. This depth difference is the main reason wavelength choice depends on the target area.
Longer wavelengths scatter less and are less absorbed by surface pigments (melanin and hemoglobin), allowing more photons to travel farther. Shorter red wavelengths deposit more energy near the surface.
This depth difference shapes how each wavelength is used:
| Feature | 660 nm (Visible Red) | 850 nm (Near-Infrared) |
|---|---|---|
| Visibility | Bright red glow | Invisible or very faint |
| Typical penetration | Shallow — mostly within the skin (a few millimeters) | Deeper — into subcutaneous tissue and muscle |
| Primary tissue target | Epidermis & upper dermis | Subcutaneous tissue, muscle, joints |
| Common research focus | Skin appearance, collagen, hair | Exercise recovery, musculoskeletal research |
| Common device formats | Facial masks, small panels, wands | Full-body panels, recovery devices |
Note: Penetration varies with skin type, tissue and device output. Depth figures quoted in device marketing are usually model estimates, not measurements of a specific product.
660nm Red Light Benefits in Research: Skin and Surface Applications
660nm red light is one of the most widely studied wavelengths in photobiomodulation research, particularly for skin and hair. Studies using specific devices and protocols have examined:
- Collagen and skin appearance: controlled studies have reported improvements in measures such as skin roughness and collagen density (e.g., Wunsch & Matuschka, 2014)
- Wound and scar research: red light is investigated in laboratory and clinical wound-healing models
- Hair: randomized, sham-controlled trials of specific low-level light devices have reported increased hair density in pattern hair loss (e.g., Jimenez et al., 2014)
- Acne and redness: red light is studied in clinical dermatology, often in combination with blue light
Note: These findings apply to the devices, settings and participants studied. They are not claims about any particular consumer product.
850nm Near-Infrared Benefits in Research: Muscles and Deeper Tissue
850nm near-infrared light is the most common NIR wavelength in devices designed for larger body areas. Because it travels deeper than 660nm, it is studied for structures below the skin, such as muscle and the soft tissue around joints.
- Exercise recovery: some trials have measured muscle-damage markers and soreness after NIR exposure around exercise (e.g., Ferraresi et al., 2012)
- Musculoskeletal research: systematic reviews have examined red and NIR light in musculoskeletal pain, with results that vary by protocol (e.g., Bjordal et al., 2003)
- Inflammation markers: laboratory studies investigate how NIR exposure affects inflammatory signaling
- Transcranial research: an early-stage research field that uses specialised clinical equipment
Clinical studies: Ferraresi et al. (2012) — NIR Muscle Recovery · Bjordal et al. (2003) — NIR for Musculoskeletal Pain
660nm vs 850nm Red Light: Side-by-Side Comparison
The following table summarizes the key differences between 660nm and 850nm red light across all major dimensions:
| Dimension | 660nm Red Light | 850nm Near-Infrared |
|---|---|---|
| Visibility | Visible bright red | Invisible (faint dim glow) |
| Penetration Depth | Shallow (skin / dermis) | Deeper (subcutaneous tissue / muscle) |
| Primary Target | Collagen, fibroblasts, follicles | Mitochondria in deep tissue |
| Common Research Focus | Skin appearance, hair | Exercise recovery, musculoskeletal |
| Device Formats | Face masks, small panels, wands | Large panels, full-body beds, therapy wraps |
| Volume of Research | Large body of skin and hair research | Smaller, growing body of musculoskeletal research |
Common Mistakes When Choosing Between 660nm and 850nm Red Light
Many buyers misunderstand the difference between 660nm and 850nm, leading to suboptimal device choices. Here are the most common mistakes:
- Myth: “850nm is more powerful than 660nm.” Fact: 850nm travels deeper but is not “more powerful.” Each wavelength suits a different tissue depth.
- Myth: “660nm is only for skin.” Fact: 660nm is also used in body devices, usually alongside NIR, because it covers the surface layers.
- Mistake: Expecting 660nm alone to reach deep structures. Fact: Visible red is mostly absorbed near the surface. Products for larger body areas usually use 850nm or a dual-wavelength layout.
- Mistake: Ignoring irradiance specs. Fact: Wavelength determines where light works; irradiance (mW/cm²) determines how much work is done.
Tip: Compare measured irradiance at a stated distance, not only the wavelength on the label.
Should You Use 660nm and 850nm Red Light Together?
For many general-purpose devices, combining both wavelengths is the practical choice. A dual-wavelength device (for example 660nm + 850nm at a 1:1 ratio) covers both the surface layers and deeper tissue in a single session, which is why most full-body panels on the market offer this combination.
| Factor | 660nm Only | 850nm Only | 660nm + 850nm |
|---|---|---|---|
| Skin Coverage | Excellent | Poor | Good |
| Deep Muscle Coverage | Poor | Excellent | Excellent |
| Typical Use in Body Devices | Less common | Common | Common |
| Overall Versatility | Limited | Limited | Best |

Explore related products: LUMETIVE Red Light Therapy Devices — 660nm & 850nm LED Therapy Solutions
How to Choose the Right 660nm or 850nm Red Light Device
Choosing between 660nm and 850nm devices depends on the product’s intended use and the body area it covers. Use this framework:
- Face and skin-focused products → 660nm-dominant face mask or small panel
- Body-area products (back, knees, shoulders) → 850nm or dual-wavelength wrap or panel for deeper reach
- General-purpose products → Dual-wavelength 660 + 850nm panel
Key specifications to check beyond wavelength: irradiance (mW/cm² at a stated distance), LED count and power, duty cycle, beam angle and warranty. A high-irradiance 660nm-only panel can deliver more light to the skin than a weak dual-wavelength panel — output matters as much as wavelength.
Key Specifications to Consider When Choosing a Red Light Therapy Device
Choosing a professional red light therapy device requires more than checking the wavelength. Key specifications such as irradiance, LED power, beam angle, duty cycle, treatment dose, and warranty determine the actual performance, coverage, and user experience.
| Specification | What It Means | How to Choose | Recommended Reference for Red Light Therapy Devices |
|---|---|---|---|
| Wavelength (nm) | Determines how deep the light travels and which device formats it suits. | Select wavelengths according to the target body area and product positioning. | 660nm Red Light: Commonly used in facial, skincare and scalp devices. 850nm Near Infrared: Commonly used in wraps and pads for knees, shoulders, back and other larger body areas. 660nm + 850nm Dual Wavelength: Common in wearable and panel devices that cover both surface and deeper tissue. |
| Irradiance (mW/cm²) | Measures the optical power density delivered to the illuminated area. | Always evaluate irradiance at the actual use distance, not only LED chip output. | Beauty & Facial Devices: 20–50 mW/cm² Wearable Devices (Hat, Mask, Gloves): 30–80 mW/cm² Recovery Devices (Wrap, Knee, Belt): 50–100 mW/cm² |
| LED Quantity | Determines coverage and light distribution uniformity. | Choose LED quantity according to the size of the illuminated area. More LEDs do not mean better performance without sufficient irradiance. | Facial Mask : 60–240 LEDs Hair Growth Cap : 150–300 LEDs Gloves : 100–200 LEDs Knee / Shoulder Wrap : 200–400 LEDs Large Body Wrap: 300–500 LEDs |
| LED Power Output | Defines the maximum optical output capability of each LED chip. | Choose high-efficiency LED chips with stable output, low heat generation, and long lifespan. | Standard Wearable Devices: 0.2W–0.5W per LED chip Professional Home Devices: 0.5W–1W per LED chip |
| Duty Cycle (%) | Defines the percentage of time LEDs emit light during pulse operation. | Check whether the manufacturer reports peak output or actual average delivered energy. | Continuous Mode: 100% duty cycle recommended for most wearable applications. Pulsed Mode: 10Hz–100Hz frequency commonly used when supported by product design. |
| Beam Angle (°) | Controls how widely light spreads from each LED. | Select beam angle according to treatment distance and coverage requirements. | Wearable Devices: 60°–90° beam angle recommended. Large Area Devices: 90°–120° for wider coverage. |
| Dose / Fluence (J/cm²) | The optical energy delivered per unit area during one session. | Evaluate together with irradiance and session time. | Published studies use a wide range of fluences that differ by application and protocol. Define a dose reference for each SKU’s intended use, and document how it was calculated. |
| Session Time | How long the device runs per session, usually set by a built-in timer. | Higher-irradiance devices reach a given dose in less time. | Lower-output devices: built-in timers of 15–30 minutes are typical Professional wearable devices: built-in timers of 10–20 minutes are typical |
| Temperature Management | Controls device surface temperature and user comfort. | Wearable products should stay at a comfortable temperature during use. | Recommended Surface Temperature: Below 42°C during normal operation. |
| Warranty Period | Reflects manufacturer confidence and product reliability. | Choose suppliers offering clear quality control and after-sales support. | Standard OEM Products: 12 months Professional / Distributor Products: 24 months recommended |
Tip: For a general-purpose range, a dual-wavelength (660 + 850nm) panel covers the widest set of uses. Match the device size to the area it is meant for — larger panels for the body, compact panels or masks for the face.
Why Wavelength Matters More Than Wattage
When choosing a red light therapy device, many buyers focus on wattage — the total power consumption of the panel. But wattage alone doesn’t determine how much useful light a device delivers. The optical window of biological tissue, the biphasic dose response reported in research and the specific wavelength selection matter far more than raw power.
The Optical Window of Biological Tissue
Biological tissue has an “optical window” between approximately 600–1000 nm where light can penetrate without being fully absorbed by water, hemoglobin, or melanin. Within this window:
- 660 nm sits near one of the absorption peaks of cytochrome c oxidase, the proposed photoacceptor in photobiomodulation research, and is absorbed close to the surface.
- 850 nm benefits from reduced scattering and absorption by surface chromophores, so it reaches deeper while still falling within the absorption range of the same photoacceptor.
Wavelengths Between 700 and 770 nm
Wavelengths between roughly 700nm and 770nm are used less often in devices, and there is less published research at these wavelengths than at 660nm or 850nm. If a product uses them (for example 740nm LEDs), ask for evidence specific to that wavelength.
The Arndt-Schulz Biphasic Dose Response
More power is not always better. Research describes a biphasic dose response in photobiomodulation, sometimes linked to the Arndt-Schulz law:
- At low doses, studies have observed stimulatory cellular responses.
- Beyond a certain point, additional energy has not produced additional effect in many studies.
- At high doses, some studies report inhibitory effects — sometimes called photoinhibition.
This is why a 100W panel with poor wavelength selection and beam distribution can deliver less useful light than a well-designed 50W panel with a sensible 660 nm + 850 nm ratio and even irradiance.
Other Wavelengths in the Photobiomodulation Spectrum
While 660 nm and 850 nm dominate the consumer market, other wavelengths appear in devices and research for different applications. Understanding them helps brands and engineers choose the right configuration for a product.
| Wavelength | Relative Penetration | Typical Device Use | Common Research Topics |
|---|---|---|---|
| 630 nm | Shallow | Face masks, cosmetic devices | Skin appearance |
| 660 nm | Shallow | Masks, scalp caps, panels | Skin appearance, collagen, hair |
| 810 nm | Deeper | Clinical lasers, some panels | Musculoskeletal, transcranial (early-stage) |
| 830 nm | Deeper | Panels, wraps | Musculoskeletal research |
| 850 nm | Deeper | Wraps, pads, panels | Exercise recovery, musculoskeletal research |
| 880 nm | Deeper | Panels | Limited published research |
| 1064 nm | Deepest of these | Clinical laser systems | Clinical research settings |
630 nm vs. 660 nm in Skin Devices
630 nm light, common in cosmetic masks, is absorbed slightly closer to the surface than 660 nm. Both appear in skin-appearance research; 660 nm is more often chosen when a design aims to reach the dermis, including the area around hair follicles.
810 nm vs. 830 nm vs. 850 nm: The NIR Nuances
These three near-infrared wavelengths are often used interchangeably, but evidence suggests subtle differences:
- 810 nm: Often used in transcranial and clinical laser research, partly because of lower water absorption than 850 nm.
- 830 nm: Used in several musculoskeletal studies; direct head-to-head comparisons with 850 nm are limited.
- 850 nm: The most common NIR LED in consumer devices, balancing depth, LED efficiency and cost.
Wavelengths to Be Skeptical About
Not all wavelengths marketed for “light therapy” have evidence behind them:
- Green (532 nm): Minimal penetration; mainly absorbed by melanin. Limited research for photobiomodulation applications.
- Yellow/Amber (590–595 nm): Used in some cosmetic devices for redness, but evidence is weak compared to red wavelengths.
- Far-infrared (>1000 nm): Primarily produces heat and works through a different mechanism from red and NIR photobiomodulation.
Safety Considerations by Wavelength
Red and near-infrared LEDs do not emit ultraviolet light, but safe use still depends on output, exposure time and eye protection — and each wavelength brings its own considerations for manufacturers and users.
Eye Protection Requirements
660 nm (Visible Red): The eyes respond to bright visible light by constricting the pupils and squinting. Direct exposure should still be avoided; follow the device’s eye-protection guidance.
850 nm (Near-Infrared): Invisible light does not trigger these natural responses — the pupils don’t constrict and you won’t squint, yet the light still reaches the retina. NIR can therefore pose a greater risk to the eyes than visible red at comparable output. Follow the model’s eye-protection requirements; goggles that block NIR are commonly recommended.
Photosensitivity and Medications
Photosensitizing medications can increase sensitivity to light therapy. Consult a healthcare provider before using red light therapy if taking:
- Tetracycline antibiotics
- Retinoids (isotretinoin, tretinoin)
- NSAIDs (ibuprofen, naproxen—mild photosensitivity)
- Diuretics
- Antipsychotics
- St. John’s Wort supplements
Skin Type Considerations (Fitzpatrick Scale)
Melanin absorption differs by skin type, affecting light penetration:
| Skin Type | Characteristics | Considerations for Red Light Therapy |
|---|---|---|
| I–II | Very fair, burns easily | Follow the device instructions |
| III–IV | Medium, tans gradually | Slightly more surface absorption; follow the manufacturer’s distance guidance |
| V–VI | Dark brown/black, rarely burns | Higher melanin absorption at the surface; follow the manufacturer’s guidance and stop if uncomfortable |
Contraindications
Avoid red light therapy or consult a healthcare provider if you have:
- Active cancer or undergoing cancer treatment (over treatment area)
- Pregnancy (over abdominal area—lack of safety data)
- Photosensitive epilepsy (rare, but flashing/pulsing light can trigger)
- Recent photosensitizing chemical peels or laser treatments
- Open wounds with active infection (wait until cleared)
Reference: The IEC 62471 photobiological safety standard classifies lamps and LED devices into risk groups. Many LED panels are assessed as Exempt or Risk Group 1 (low risk), but the classification must come from the specific device’s assessment — high-output panels can fall into Risk Group 2.
For Brands & Manufacturers: What the Spec Sheet Doesn’t Tell You
As a manufacturer or brand sourcing red light therapy devices, the wavelength specification is only the starting point. Understanding LED binning, ratio engineering, and certification requirements ensures you deliver products that actually perform as advertised.
LED Binning and Wavelength Tolerance
LED manufacturers sort chips into “bins” based on wavelength, forward voltage, and luminous flux. A specification of “660 nm ± 10 nm” means LEDs could range from 650–670 nm. For consistent products:
- Tight binning (±5 nm) ensures consistent performance across production batches.
- Loose binning (±10–15 nm) may place some LEDs outside the intended wavelength range.
- Request 3-bin matching from your LED supplier for critical applications.
Ratio Engineering: What 1:1, 2:1, and 4:1 Actually Mean
The ratio of 660 nm to 850 nm LEDs in a panel sets its design bias:
| Ratio (660:850) | LED Distribution | Best For |
|---|---|---|
| 1:1 | 50% red, 50% NIR | General-purpose devices, mixed skin and body use |
| 2:1 | 66% red, 33% NIR | Skin-focused applications, facial devices |
| 1:2 | 33% red, 66% NIR | Body-area and recovery-oriented devices |
| 4:1 | 80% red, 20% NIR | Cosmetic and facial devices |
Reading Spectral Test Reports
Ask your manufacturer for spectral test reports (from an integrating sphere). Check:
- Peak wavelength: Should match specification (±5 nm acceptable).
- FWHM (Full Width at Half Maximum): Narrower is better (20–30 nm is typical for photobiomodulation LEDs).
- Secondary peaks: Some cheap LEDs have unwanted secondary emission peaks that waste energy.
- Total radiant flux: Verify against advertised power.
Certification Planning: CE, FCC, ETL, and IEC 62471
Different markets require different certifications:
- CE (Europe): Required for EU market; includes EMC and safety testing.
- FCC (USA): Electromagnetic interference compliance for electronic devices.
- ETL/UL: Electrical safety certification; ETL is often faster and less expensive than UL.
- IEC 62471: Photobiological safety standard for lamps and lamp systems; commonly requested by retailers, importers and test laboratories.
Pro tip: Design for the strictest standard first (typically IEC 62471 Risk Group 1), then add market-specific certifications. Retrofitting thermal management or safety interlocks after design is expensive.
How to Compare 660nm and 850nm Red Light Devices for OEM Projects
Review wavelength data, measured optical performance, dose calculation, coverage uniformity, and compliance documents—not just LED count or rated wattage.
Peak Wavelength vs. Spectral Bandwidth What does 660nm or 850nm actually mean?
Nominal wavelength usually refers to peak wavelength.
A label such as 660nm, 630nm, 810nm, or 850nm normally refers to the LED’s peak emission wavelength. It does not mean that the LED emits light at one perfectly fixed and infinitely narrow wavelength.
LED output has a measurable spectral distribution around its peak. Professional OEM evaluation should therefore consider the actual spectrum of the finished device, not only the nominal value in a marketing specification or LED datasheet.
- Peak wavelength and allowed production tolerance
- Spectral bandwidth, such as full width at half maximum (FWHM)
- Whole-device spectral testing, not only individual LED claims
- LED binning and wavelength consistency between production batches
- Test method, test instrument, and documented testing conditions
Wavelength Combination How should wavelength configurations be selected?
Select red and NIR ratios according to product positioning.
There is no universal red-to-near-infrared ratio that fits every product, user scenario, device format, or market. A suitable wavelength configuration should be based on the intended device category, target user group, optical design, control functions, and commercial positioning.
| Product direction | Wavelength configuration logic | OEM design priorities |
|---|---|---|
| Skin-focused devices | Often red-light dominant, using 630nm and/or 660nm with optional NIR support. | Face fit, eye comfort, close-distance uniformity, temperature management. |
| Recovery-focused devices | Often NIR dominant, using 810nm, 830nm, and/or 850nm with red-light support. | Coverage area, output at intended distance, heat dissipation, channel control. |
| General-purpose panels | A balanced red / NIR layout or separately controllable red and NIR channels. | Multi-distance irradiance data, treatment area, output uniformity. |
| Custom OEM / ODM projects | Defined according to target users, device format, budget, and market requirements. | LED layout, wavelength ratio, firmware logic, MOQ, and compliance scope. |
Device Performance Which specifications actually matter?
Rated LED wattage is not the same as delivered optical performance.
A high LED count or high stated LED wattage does not automatically mean a device delivers higher usable output. Buyers should compare actual electrical consumption, measured irradiance, test distance, treatment area, output uniformity, and thermal design together.
| Specification | What it means | What buyers should confirm |
|---|---|---|
| LED rated power | The nominal electrical rating of an individual LED. | Do not treat it as actual operating power or actual optical output. |
| Actual power consumption | The electrical power consumed by the complete device. | Confirm voltage, operating mode, brightness level, and adapter configuration. |
| Irradiance | Optical power received per unit area, often stated in mW/cm². | Require test distance, test mode, instrument type, and measurement grid. |
| Treatment area | The usable illuminated area at a stated distance and output threshold. | Clarify whether it refers to maximum area, effective area, or uniform area. |
| Uniformity | How consistently optical output is distributed across the treatment area. | Request irradiance mapping with minimum, maximum, and average values. |
Dose Calculation How do irradiance and time determine fluence?
Fluence is calculated from measured irradiance and exposure time.
Fluence expresses the amount of optical energy delivered per unit area. For product comparison and protocol-reference purposes, it should be calculated using measured irradiance at a defined distance.
If irradiance is expressed in mW/cm², use this practical conversion: Fluence (J/cm²) = Irradiance (mW/cm²) × Time (s) ÷ 1000
Example: If measured irradiance is 50mW/cm² at a stated distance, and the operating time is 10 minutes (600 seconds), the calculated fluence is 30J/cm².
- Distance, angle, body contour, and device positioning affect actual received energy
- Center-point output does not represent the entire treatment area
- Irradiance mapping should support fluence references for larger treatment areas
- Use dose-reference data as an engineering comparison tool, not as a universal treatment claim
OEM Documentation What technical documents should an OEM supplier provide?
Documentation should verify performance and support market entry.
A capable OEM supplier should provide technical records that correspond to the final SKU, electrical configuration, target market, intended use, and applicable product claims.
| Documentation category | Typical files to request | Why it matters |
|---|---|---|
| Optical performance | Spectral reports, peak wavelength data, irradiance testing, irradiance mapping, uniformity data. | Verifies the product’s measurable optical performance. |
| Electrical and safety | Input-power data, adapter specifications, temperature-rise information, applicable safety reports. | Supports electrical design review and safety assessment. |
| EMC and materials | EMC, LVD or relevant safety files, RoHS, REACH, and material declarations. | Supports customer audits and target-market compliance review. |
| Quality control | Quality-system records, incoming inspection, aging tests, AQL, traceability, warranty policy. | Evaluates manufacturing consistency and supply-chain reliability. |
| Market-specific documentation | Files applicable to CE, FCC, UKCA, FDA/EPA, or other destination-market requirements. | Helps align the product with its intended market pathway. |
660nm and 850nm Red Light Device Buyer Checklist
Use this checklist when comparing suppliers, reviewing quotations, or preparing an OEM / ODM product specification.
- Confirm whether stated wavelengths refer to peak wavelength and request spectral test data
- Choose red and NIR ratios according to product category and intended user scenario
- Request measured irradiance at clearly stated distances and operating modes
- Ask for irradiance mapping instead of relying only on center-point measurements
- Calculate fluence using measured irradiance and planned exposure time
- Confirm actual electrical power consumption, not just LED rated wattage
- Review applicable safety, EMC, RoHS, REACH, and target-market documentation
- Verify whether existing certificates remain applicable after OEM customization
Need help selecting a 660nm / 850nm configuration?
Tell us your product type, target market, required certifications, estimated quantity, and customization requirements. Lumetive can provide OEM / ODM configuration guidance and relevant technical documentation.
Request Technical DocumentsFrequently Asked Questions
Why can’t I see the 850nm lights on my panel? Is it broken?
No, your panel is not broken. 850nm is near-infrared light and is invisible or only faintly visible to the human eye. The red glow you see comes from the 660nm LEDs. This is completely normal and one of the most common questions first-time users ask.
Do I really need both 660nm and 850nm, or is one enough?
It depends on what the device is for. 660nm is absorbed mainly in the skin, while 850nm reaches deeper tissue. A dual-wavelength device covers both depths in one format, which makes it the more flexible choice for general-purpose use; a face-only device often doesn’t need 850nm.
Is 850nm better for muscle recovery and joint pain?
850nm reaches deeper tissue than 660nm, which is why it is common in body wraps and recovery-oriented devices and appears in exercise-recovery and musculoskeletal research. Study results vary with the device and protocol, so a wavelength alone doesn’t make a device effective. For joint pain or any other condition, talk to a healthcare professional.
Should I turn off 850nm when using the panel on my face?
Follow the instructions for your model. Some devices let you switch to 660nm-only for facial use, which keeps the light focused on the skin. Whichever setting you use, wear the recommended eye protection.
Do I need eye protection with 850nm?
Yes, especially with higher-output devices. Because 850nm is invisible, your eyes have no natural protective reflex (no squinting or pupil constriction). Use the eye protection specified for the device whenever NIR is active.
How deep does 850nm actually penetrate compared to 660nm?
660nm is absorbed mostly within the skin, while 850nm travels several times further into subcutaneous tissue and muscle. Exact depths depend on skin type, tissue and device output, and only a small fraction of the light reaches the deepest layers.
Does 850nm feel warmer or produce more heat?
Many users notice mild warmth from devices with 850nm LEDs, though much of it comes from the LEDs and electronics themselves. Red and NIR devices are not designed as heat therapy and work differently from far-infrared heating; stop if a device feels uncomfortably hot.
Can I use 660nm + 850nm red light therapy every day?
Many consumer devices are designed for regular, short sessions. Follow the frequency, session length and distance in your model’s manual, and stop if you experience discomfort. If you are sensitive to light or take light-sensitizing medication, check with a healthcare professional first.
Which wavelength is better for hair growth — 660nm or 850nm?
Most hair research has used red wavelengths in the 630–680nm range, delivered by specific low-level laser or LED caps and combs. 850nm appears in some devices as a supporting wavelength, with less research behind it for hair.
Is a dual-wavelength panel worth the extra money?
It depends on the use. Dual 660nm + 850nm devices are more versatile because one device covers both surface and deeper tissue. If a product will only be used on the face, a red-only device may be enough.
What is the main difference between 660nm and 850nm?
660nm is visible red light that is absorbed mainly in the epidermis and upper dermis. 850nm is invisible near-infrared light that reaches deeper into subcutaneous tissue and muscle. Both are thought to act on the same mitochondrial photoacceptor, but at different depths.
How long should each session be?
Follow the session length set for your device — most consumer devices use built-in timers of about 10–20 minutes. Published study protocols vary widely in duration, frequency and distance, so settings from a study or another device may not apply to yours.
Will 660nm or 850nm cause tanning or skin damage?
Neither wavelength contains ultraviolet (UV) light, so they do not cause tanning or UV-related sunburn. That doesn’t mean any intensity or duration is safe — follow the device’s safety instructions.
How soon will I see results from 660nm vs 850nm?
There is no universal timeline. As a reference point, skin-appearance studies typically assess outcomes after 8–12 weeks of repeated sessions, while exercise-recovery studies often measure soreness 24–48 hours after exercise. These are study timelines, not promises for any device.
Should I choose a panel with only 660nm, only 850nm, or both?
Choose a red-dominant (660nm) device for face and skin-focused use, an NIR or dual device for larger body areas, and a dual-wavelength 660nm + 850nm device for general-purpose use. Either way, check the measured output and instructions for the exact model.
Research references
- Cleveland Clinic — Red Light Therapy Overview Cleveland Clinic ↗
- Hamblin MR (2016) — Photobiomodulation Mechanisms PubMed ↗
- Ferraresi et al. (2012) — NIR Muscle Recovery PubMed ↗
- Bjordal et al. (2003) — NIR for Musculoskeletal Pain PubMed ↗
Related articles
Planning a product range?
Compare configurations and request the current Lumetive catalog.